
Treatment consent form: a general template plus forms for PMU, laser, lashes and peels
A general treatment consent template and four complete forms — permanent make-up, laser and IPL, lashes and chemical peels — with yes/no points to sign.
A treatment consent form is a conversation about risk, written down so the client hears it before the treatment and you can show it afterwards. Below you will find what it needs to cover, a general template and four complete consent forms: permanent make-up, laser hair removal and IPL, lash extensions and lifts, and chemical peels.
What a treatment consent form should include
- What the treatment involves and a realistic result — how it works and how many sessions it may take.
- Specific side effects — for this treatment, not a vague “complications may occur”.
- Contraindications confirmed by the client — lists for each treatment group are in Contraindications to beauty treatments.
- Aftercare and who to call if something worries her.
- A declaration that the consultation is accurate — how to build one is covered in Beauty consultation form: questions to ask.
- A chance to ask questions and to change her mind before the treatment starts.
- Date and signatures — the client’s and the therapist’s; for anyone under 18, a parent or legal guardian signs.
Treatment consent is not GDPR consent (RODO, as it is called in Poland). That one is about data — health data, photos, marketing — you collect it separately, and the treatment can never depend on marketing consent.
Write each risk as a separate sentence with a “yes / no” answer. The client answers each one instead of signing a paragraph of small print — and a form built like this moves into the app point by point.
Beauty treatment consent form template
For Polish-speaking clients, use the Polish version — it is in the Polish version of this article.
Copy it and adapt it to your salon:
TREATMENT CONSENT — [salon name], [address], NIP [tax ID]
Client’s full name:Date of birth:
Treatment:Area:
Therapist:
Tick “yes” or “no” for each point:
- 1.I know what the treatment involves, what it is for and how many sessions it may take.☐ yes ☐ no
- 2.I understand that the result depends on my skin and body and may differ from what I expect.☐ yes ☐ no
- 3.I have been told about possible side effects: ☐ yes ☐ no
- 4.I have been shown the list of contraindications and none of them applies to me.☐ yes ☐ no— if no, which:
- 5.The information in my consultation is true and complete.☐ yes ☐ no
- 6.I have received aftercare advice. If I notice anything worrying, I will contact the salon: [phone].☐ yes ☐ no
- 7.My questions have been answered. I know I can change my mind before the treatment starts.☐ yes ☐ no
- 8.I consent to the treatment.☐ yes ☐ no
Date:
Client’s signature:
Therapist’s signature:
For a client under 18: As parent / legal guardian, I consent to the treatment of [minor’s full name].
Guardian’s full name:
Signature:
Consent forms for common treatments — templates
Each form below complements the consultation — it doesn’t replace it. Treat the risks and aftercare as a starting point: add what the pigment, product or device manufacturer tells you, and fill in the numbers in square brackets from your own practice.
Permanent make-up consent form
PERMANENT MAKE-UP CONSENT — [salon name], [address], NIP [tax ID]
Client’s full name:Date of birth:
Area:☐ brows ☐ lips ☐ upper eyeliner ☐ lower eyelinerTechnique:
Therapist:
Tick “yes” or “no” for each point:
- 1.I know that permanent make-up means implanting pigment into the skin and that a top-up is usually needed after [X] weeks.☐ yes ☐ no
- 2.I know that the colour straight after the treatment differs from the healed colour, and that over time the pigment fades and may change tone.☐ yes ☐ no
- 3.I have been told that swelling, redness and small scabs may appear in the first few days.☐ yes ☐ no
- 4.For lips: I know the treatment can trigger a cold sore.☐ yes ☐ no ☐ not applicable
- 5.I know that removing pigment takes separate treatments and is not always complete.☐ yes ☐ no
- 6.The shape and colour were agreed with me before the treatment started.☐ yes ☐ no
- 7.None of the following applies to me: pregnancy or breastfeeding, an active cold sore in the area, a tendency to keloid scarring, a clotting disorder or anticoagulants, a skin condition or inflammation in the area, filler or botulinum toxin near the area in the last [X] weeks.☐ yes ☐ no— if no, which:
- 8.None of the general contraindications applies to me either: poorly controlled diabetes, cancer under active treatment, epilepsy, isotretinoin.☐ yes ☐ no— if no, which:
- 9.The information in my consultation is true and complete.☐ yes ☐ no
- 10.I have received aftercare advice: [salon’s aftercare]. If I notice anything worrying, I will contact the salon: [phone].☐ yes ☐ no
- 11.My questions have been answered. I know I can change my mind before the treatment starts.☐ yes ☐ no
- 12.I consent to the permanent make-up treatment.☐ yes ☐ no
Date:
Client’s signature:
Therapist’s signature:
Laser treatment consent form — laser hair removal and IPL
LASER HAIR REMOVAL / IPL CONSENT — [salon name], [address], NIP [tax ID]
Client’s full name:Date of birth:
Area:Device:☐ laser ☐ IPL
Therapist:
Tick “yes” or “no” for each point:
- 1.I know that results need a course of treatments and that the number depends on my skin and hair.☐ yes ☐ no
- 2.I have been told that redness and swelling may appear in the treated area.☐ yes ☐ no
- 3.I have been told about the risk of burns, hyperpigmentation or hypopigmentation — higher on tanned skin.☐ yes ☐ no
- 4.I know that for [X] weeks before and after the treatment I must avoid the sun, sunbeds and fake tan and use sun protection.☐ yes ☐ no
- 5.I know that tattoos and moles in the area will be avoided.☐ yes ☐ no
- 6.None of the following applies to me: a fresh tan or fake tan, photosensitising medication or isotretinoin, pregnancy, epilepsy, an infection, cold sore or inflammation in the area.☐ yes ☐ no— if no, which:
- 7.None of the general contraindications applies to me either: breastfeeding, poorly controlled diabetes, cancer under active treatment.☐ yes ☐ no— if no, which:
- 8.The information in my consultation is true and complete.☐ yes ☐ no
- 9.I have received aftercare advice: [salon’s aftercare]. If I notice anything worrying, I will contact the salon: [phone].☐ yes ☐ no
- 10.My questions have been answered. I know I can change my mind before the treatment starts.☐ yes ☐ no
- 11.I consent to the treatment.☐ yes ☐ no
Date:
Client’s signature:
Therapist’s signature:
Lash extension and lash lift consent form
LASH EXTENSION / LASH LIFT CONSENT — [salon name], [address], NIP [tax ID]
Client’s full name:Date of birth:
Treatment:☐ lash extensions ☐ lash lift
Therapist:
Tick “yes” or “no” for each point:
- 1.I have been told that eye irritation, watering and redness may occur during and after the treatment.☐ yes ☐ no
- 2.I know that an allergic reaction to the adhesive or lift solutions can happen even in people who have never had one before.☐ yes ☐ no
- 3.For a lift: I know my lashes may become dry or weaker.☐ yes ☐ no ☐ not applicable
- 4.I know that for [X] hours after the treatment I must avoid water and steam and not rub my eyes.☐ yes ☐ no
- 5.I know I must not remove extensions myself — removal is done at the salon.☐ yes ☐ no ☐ not applicable
- 6.I will take out contact lenses for the treatment.☐ yes ☐ not applicable
- 7.None of the following applies to me: an eye or eyelid infection or inflammation, an allergy to adhesive, acrylates or product ingredients, recent surgery or a treatment around the eyes, sensitive eyes or constant watering.☐ yes ☐ no— if no, which:
- 8.None of the general contraindications applies to me either: pregnancy or breastfeeding, poorly controlled diabetes, cancer under active treatment, epilepsy, isotretinoin.☐ yes ☐ no— if no, which:
- 9.The information in my consultation is true and complete.☐ yes ☐ no
- 10.I have received aftercare advice. If I notice anything worrying, I will contact the salon: [phone].☐ yes ☐ no
- 11.My questions have been answered. I know I can change my mind before the treatment starts.☐ yes ☐ no
- 12.I consent to the treatment.☐ yes ☐ no
Date:
Client’s signature:
Therapist’s signature:
Chemical peel consent form
CHEMICAL PEEL CONSENT — [salon name], [address], NIP [tax ID]
Client’s full name:Date of birth:
Product and strength (filled in by the salon):
Therapist:
Tick “yes” or “no” for each point:
- 1.I know that a chemical peel removes the top layer of skin in a controlled way with an acid product, and that results usually need a course of treatments.☐ yes ☐ no
- 2.I have been told that I may feel burning or tingling during the treatment and that redness, tightness and peeling may follow.☐ yes ☐ no
- 3.I have been told about the risk of irritation and hyperpigmentation — especially if my skin is exposed to the sun afterwards.☐ yes ☐ no
- 4.I know that for [X] days after the treatment I must use sun protection, avoid the sun, sunbeds and saunas, and not pick at peeling skin.☐ yes ☐ no
- 5.None of the following applies to me: a course of isotretinoin or recent use of retinoids, an active cold sore, wounds, irritation or broken skin in the area, a fresh tan, an allergy to the product’s ingredients, pregnancy or breastfeeding (for products where this is a contraindication).☐ yes ☐ no— if no, which:
- 6.None of the general contraindications applies to me either: poorly controlled diabetes, cancer under active treatment, epilepsy.☐ yes ☐ no— if no, which:
- 7.The information in my consultation is true and complete.☐ yes ☐ no
- 8.I have received aftercare advice: [salon’s aftercare]. If I notice anything worrying, I will contact the salon: [phone].☐ yes ☐ no
- 9.My questions have been answered. I know I can change my mind before the treatment starts.☐ yes ☐ no
- 10.I consent to the chemical peel.☐ yes ☐ no
Date:
Client’s signature:
Therapist’s signature:
How to do it in Terminka
In Terminka’s electronic client records, a treatment consent form is a treatment record signed by the client, not a separate document type. Here is how to move any form from this article into the app:
- Start from a ready-made template. In Client card settings → Card templates → Ready-made templates, pick for example “Permanent makeup brows”, “Laser hair removal”, “Lash extensions”, “Lash lift” or “Chemical peel” and tap Create based on this — you now have your own copy to edit.
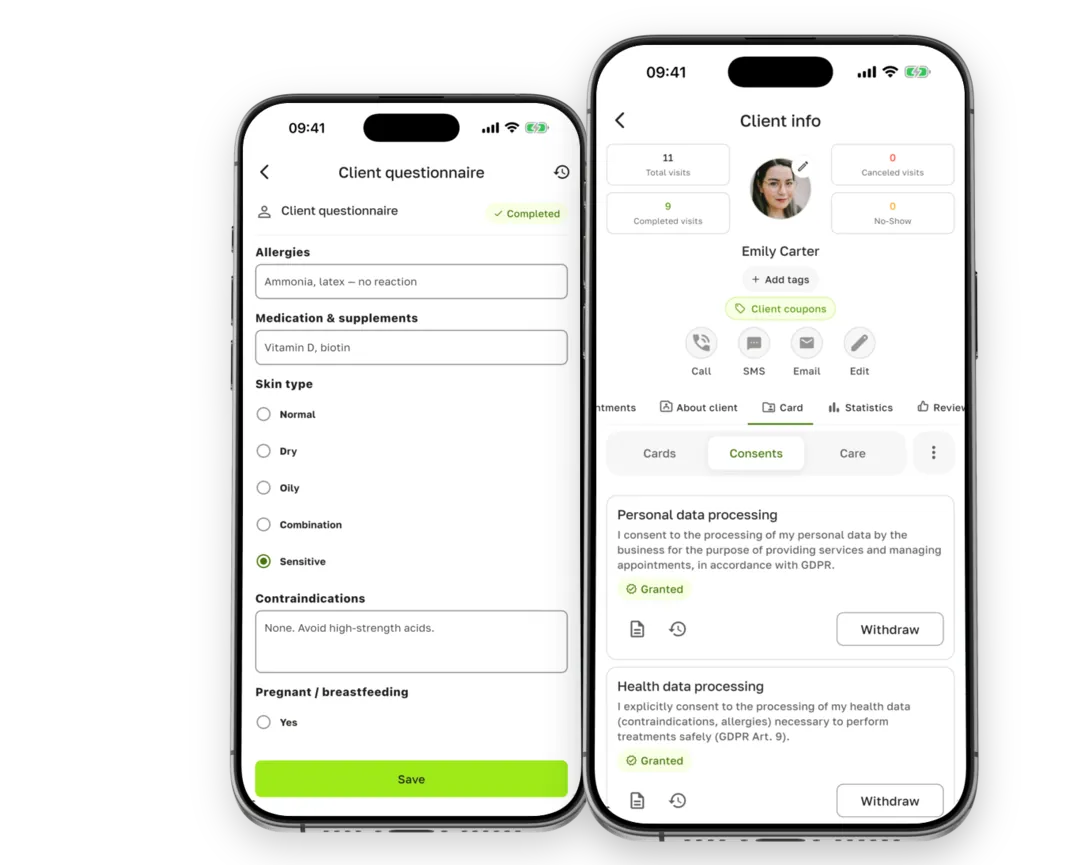
- One point, one field. Add field → type Yes / No, and put the whole sentence in the field’s label, for example “I have been told about the risk of burns, hyperpigmentation or hypopigmentation”. A Yes / No field has just two answers, so add points with “not applicable” as Single choice, and the “if no, which…” note and any blanks as a separate Text field. Fields are optional by default — mark each one Required. The PDF contains field labels and the client’s answers; text you only put in Hint under the field does not make it into the document.
- Require a signature and attach it to a service. Tick Requires signature, switch on Auto-suggest on booking and choose the Services that need consent. In the visit, the Documents and care block shows Needs action until the client has a signed consent from that template. Consent from a ready-made template doesn’t expire — to renew it, set Card validity.
- The client signs. In the salon, choose Hand the device to the client — she signs with her finger (On-screen signature) or with an SMS code. Remotely, send an SMS link or Email link, or show a QR in room — the form opens in her browser, with no app.
- The document stays in the record. A signed consent is marked Signed and saved under Client info → Card → Cards as a PDF with the questions, answers and template version — it can’t be changed after signing. Next to it, in the Consents tab, you will find ready-made GDPR consents: personal data processing, explicit consent to health data (art. 9 GDPR), email marketing, storing photos and, separately, publishing them.
Frequently asked questions about treatment consent
Is consent signed on a phone or via a link valid?
GDPR does not require any particular form of consent — what matters is that you can show what the client signed and when. With treatment consent it is the same: it is about evidence. An electronic consent form is good evidence if it keeps the full wording and its version, the date and time of signing, can’t be changed afterwards and is linked to a specific visit. A finger signature or SMS code is not, however, a qualified electronic signature. If you require written form for a document — for example because a doctor who works in your salon has decided so — stay with paper and add a scan to the client record.
Who signs for a client under 18?
A parent or legal guardian. In Terminka the guardian signs the record in the salon, and you enter their full name in the Signed by field — it goes into the document. Use On-screen signature here: an SMS code goes to the client’s phone, not the guardian’s. Add the guardian sentence from the general template to the record as a separate field.
What about aesthetic medicine?
Botulinum toxin and filler injections should be performed by a doctor or dentist — and it is the doctor who prepares the consent form and explains the risks. That is why there is no template here.
A ready-made treatment record with a signature is already in Terminka — add the points from the templates above as “Yes / No” fields, and your client signs an online consent form on a phone or via a link. It comes with the Solo plan, and after signing up you get 14 days of all features for free.
